Column · @trentongxsu100
Tailored Routines: How Small Senior Houses Personalize Activities of Daily Living
Business Name: BeeHive Homes of Lamesa TX
Address: 101 N 27th St, Lamesa, TX 79331
Phone: (806) 452-5883
BeeHive Homes of Lamesa
Beehive Homes of Lamesa TX assisted living care is ideal for those who value their independence but require help with some of the activities of daily living. Residents enjoy 24-hour support, private bedrooms with baths, medication monitoring, home-cooked meals, housekeeping and laundry services, social activities and outings, and daily physical and mental exercise opportunities. Beehive Homes memory care services accommodates the growing number of seniors affected by memory loss and dementia. Beehive Homes offers respite (short-term) care for your loved one should the need arise. Whether help is needed after a surgery or illness, for vacation coverage, or just a break from the routine, respite care provides you peace of mind for any length of stay.
101 N 27th St, Lamesa, TX 79331
Business Hours
Walk into a well run small senior home at 8 a.m. And you will not see a single, rigid schedule used to everybody. One resident is completing oatmeal and coffee at the warm kitchen table. Another is still in bed, listening to jazz with the curtains half drawn. Somebody else is already dressed and folding laundry by choice, because it makes them feel beneficial. Same time of day, 3 very different mornings.
That is the quiet power of personalized activities of daily living in a small setting. The jobs sound standard on paper, however in practice they are how individuals experience their day: rising, bathing, dressing, using the restroom, moving around, consuming meals, handling medications. When those routines are tailored in a thoughtful assisted living or board and care home, they preserve dignity and identity rather of stripping it away.
Over the previous two decades working in senior care, I have seen large centers with gorgeous amenities, and I have seen 6 bed homes tucked into regular areas. The smaller homes do not constantly win on décor or gym devices, however they typically exceed bigger operations on one crucial measurement: the capability to adjust daily care around someone at a time.
What "small senior homes" really look like
Families utilize various terms: small assisted living, residential care home, board and care, adult household home. Regulations vary by state, however the general image is similar. A typical home serves between 4 and 16 homeowners, frequently in a transformed single family house or a purpose constructed small residence. Personnel work in close proximity to residents, sharing typical spaces, aiding with meals, and supporting day-to-day routines.
Compared with a 60 or 120 bed assisted living neighborhood, a small home starts with a number of built in benefits for customizing care:
Staff ratios are typically tighter. Rather of one caretaker for 12 to 20 locals, you may see one caretaker for 3 to 6 residents throughout the day. In the evening, a single caregiver may cover the whole home, however still with far less people to monitor.
Documentation is easier and more personal. Care plans are not just electronic charts. In excellent homes, they reside in the personnel's memory, in the posted notes on the refrigerator, in the way early morning shift advises night shift about a resident's brand-new preference for chamomile instead of black tea.
The environment behaves like a household, not a hotel. The line in between "my room" and "the common area" feels closer to family life, which permits regimens to flow more naturally. Residents can gravitate to their preferred spots without passing through long passages or formal dining rooms.
These structural functions matter due to the fact that they make it possible to differ one-size-fits-all regimens. If you only have 6 individuals to wake, shower, dress, and serve breakfast, you can afford to let someone sleep till 9 a.m. You can spend ten extra minutes helping another resident pick a favorite attire instead of rushing to strike a seat count in the dining room.
Activities of day-to-day living as identity, not simply tasks
Healthcare specialists often divide day-to-day function into "ADLs" and "IADLs." It sounds medical. In practice, each of those ADLs brings a piece of who the individual is and how they see themselves.
Bathing can be a vulnerable moment or a small high-end. A retired mechanic who prided himself on self sufficiency may withstand aid in the shower because it feels like a loss of self-reliance, while another resident finds comfort in a caregiver who understands simply how warm to make the water and which lavender soap she likes.
Dressing is not just about remaining warm and covered. Clothing ties to self-respect, modesty, cultural background, even previous roles. I still keep in mind a previous bank supervisor who relaxed visibly when personnel understood he required a pushed button down t-shirt, even with elastic waist pants, to feel "prepared for the day."
Toileting and continence discuss embarassment and privacy. Poorly handled, they are a huge source of distress. Handled respectfully, with proactive timing and quiet support, they become one more regular that preserves confidence instead of wearing down it.
Mobility is autonomy. Whether somebody walks independently, uses a walker, or needs a wheelchair, the concerns are the exact same: How can we keep them moving safely, and how can we prevent turning them into a passive passenger in their own life?
Feeding and meals represent far more than calories. They are social time, sensory experience, and memory triggers. Small senior homes that prepare in an open cooking area, with gives off onions sautéing or cookies baking, use that psychological layer of care.
Medication management is frequently the least individual part of the day in large settings. In smaller homes, the exact same caregiver may know how to pair tablets with a joke or a preferred muffin, and might notice subtle modifications in how a resident swallows or reacts.
Treating these tasks as identity minutes, not only as care responsibilities, is the starting point genuine personalization.
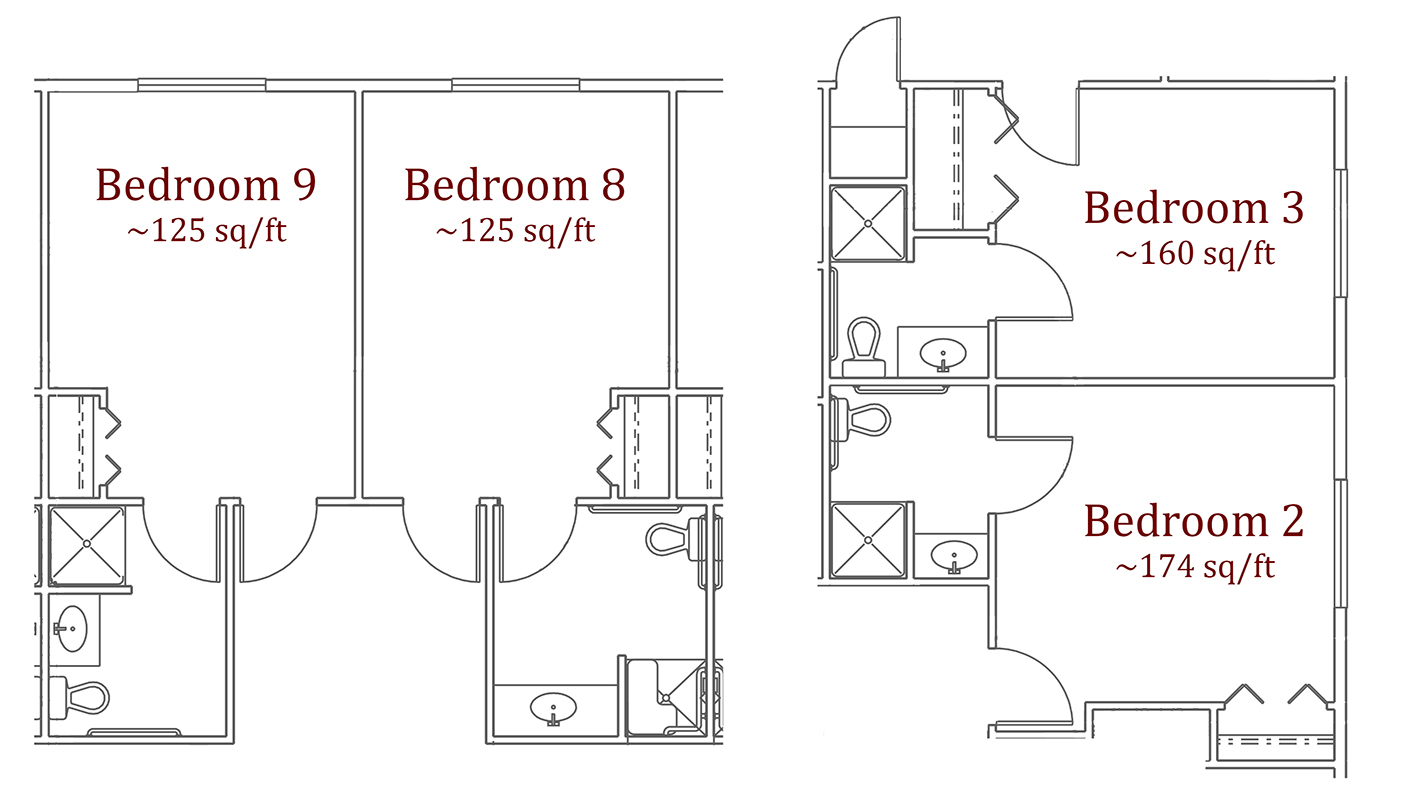
How small homes learn each resident's "default setting"
Personalization does not take place by mishap. The very best small homes build it on a few key practices.
First, they take intake seriously. I have actually seen admissions made with a clipboard in 20 minutes, and I have actually seen them take 2 hours around a dining table with tea and family photos. The 2nd approach produces much better care. Staff ask not only "Can you shower yourself?" however "Do you prefer showers or baths? Early morning or evening? Alone or with the door partially open so you can hear the TV?" For somebody with dementia, households typically fill in the spaces about lifelong habits.
Second, they create a working bio. It might be an official "life story" document or just a personnel culture of informing stories about residents throughout shift modification. A note like "Julia taught second grade for 30 years and dislikes being hurried" has direct ramifications for how you manage her mornings.
Third, they enjoy and change over the first weeks. What a resident or family reports on the first day does not constantly match reality in a new setting. Stress and anxiety, unfamiliar restrooms, different beds, or new medications can move sleep patterns and continence. Small personnels frequently observe quickly, because the individual is not one of many at the end of a long hallway. If Mr. Lopez declines his 7 a.m. Shower three mornings in a row, caretakers can recommend a late senior living morning or night regular almost immediately.
Finally, they give frontline personnel real authority. In big facilities, caregivers may have little space to deviate from the printed schedule. In well managed small homes, the administrator expects caregivers to improvise within reason and to restore ideas that worked. That autonomy is important for tailoring.
Morning regimens: awakening as yourself
Mornings reveal very quickly whether a small home genuinely individualizes care or merely repeats a smaller version of institutional routines.
I recall 2 locals from the same home who might not have been more various. One, a retired nurse in her late seventies, woke naturally at 5:30 a.m. Her whole adult life. She took pleasure in the quiet and liked to shower early, have coffee, and watch the early news. The other, a former musician in his eighties, had been a lifelong night owl. Requiring him out of bed before 9 a.m. Made him irritable and confused.
In a larger building with 80 citizens, both might get a standard 7 a.m. Wake up and 8 a.m. Breakfast since the staffing design requires it. In the small home where they lived, the over night caregiver began the nurse's shower at 6 a.m. By choice, then sat her at the kitchen area table with coffee before the day shift gotten here. The artist had a care plan that specifically mentioned "Do not wake before 8:30 unless clinically essential." His first hour of the day was purposefully slow and disorganized, with breakfast prepared when he was completely awake.
That sort of difference depends on small details: knowing who sleeps gently, who requires a mild voice or a discuss the shoulder rather of intense lights, who chooses to select their own clothing versus having two attires laid out. With time, caretakers in a small home discover these subtleties practically the way relative do. Waking up becomes something that happens with somebody, not to them.
Bathing and grooming: privacy, convenience, and cultural respect
Bathing is one of the most individual ADLs, and one where poor handling can rapidly result in rejections, agitation, or outright fear, specifically in homeowners with dementia.
Small senior homes have a simpler time matching bathing regimens to personal history. For instance, numerous older grownups grew up without day-to-day showers. Requiring a shower every early morning might feel intrusive and even unneeded to them. In a six bed home, it is completely practical to arrange baths two or 3 times a week for those residents, while still providing day-to-day face washing, oral care, and grooming.
Cultural and religious norms likewise matter. Some residents prefer exact same gender caregivers for bathing. Others have particular expectations around modesty, such as keeping particular body parts covered as much as possible. In a small home, staffing and scheduling can often appreciate these requirements, rather than treating them as inconvenient.
Temperature and sensory sensitivity play a useful function. I have seen aggressive "habits" vanish when we stopped hurrying somebody into a cold bathroom and rather warmed the room, laid out thick towels in their preferred color, and played soft music. These are small, low-cost adjustments, however they require time and attention.
Grooming routines, like shaving, hair styling, or makeup, are typically overlooked in larger settings. In small homes, I have actually watched caretakers find out precisely how one resident liked her lipstick and earrings before church, or how another preferred a hot towel shave every other day. These are not luxuries. They are methods of stating, "You are still you."
Dressing and continence: function without compromising dignity
Clothing options illustrate the trade-off between security, benefit, and self expression. A resident at danger of falls might need tough shoes and easy to put on pants, but that does not instantly suggest institutional sweats. In small homes, personnel typically have time to assist homeowners adjust their own style using flexible waist slacks, adaptive shirts with concealed Velcro, or layered clothing for warmth.
I keep in mind a lady who had constantly used coordinated outfits with jewelry. In her very first week in a small home, staff noticed her state of mind enhanced when they included her in selecting a headscarf and necklace each morning, even when they eventually needed to secure the clasp for her. That minute or more of involvement was an ADL intervention, not fluff.
Toileting and continence care advantage greatly from close observation. In a big facility, arranged toileting may happen every two hours on a stiff round. In a small home, caretakers can sync restroom offers with the individual's natural pattern: right after breakfast and lunch, before short strolls, before bed. They quickly learn subtle indications that someone needs the bathroom but might not verbalize it, such as restlessness or particular fidgeting.
The distinction in between an "accident susceptible" resident and a mainly continent person often comes down to this type of proactive, individualized timing. It lowers embarrassment, skin breakdown, and urinary infections. Households in some cases underestimate how much calmer a parent will be when they no longer reside in worry of public accidents.
Mobility and "built in" activity
In small senior homes, motion is not restricted to arranged workout classes. The really design encourages short, significant journeys: from bedroom to kitchen area, from preferred chair to garden, from living room to mailbox. For citizens with mobility challenges, caretakers can weave these movements into ADLs in subtle ways.
For a person who utilizes a walker, personnel might place the coffee pot just far enough from the table to motivate a brief walk, with close supervision, each morning. Instead of wheeling somebody to the restroom, they may enable additional time and stand-by assistance so the resident can walk with a gait belt.
What looks like "aiding with ADLs" on a care strategy can function as low level, regular physical therapy. The key is to strike a balance between safety and autonomy. Small homes, with far less homeowners to supervise, can legally offer a single person an additional five minutes to walk at their pace rather than pressing a wheelchair to save time.
I have also seen the way small teams notice changes early: a small shuffle, slower transfers, new hesitation on stairs. That early detection enables timely doctor visits, medication evaluations, and possibly home based physical therapy, instead of awaiting a fall and an emergency room visit.
Mealtime regimens: more than 3 arranged seatings
Meals in small senior homes look various from dining establishment style dining in large assisted living communities. The kitchen area is generally close adequate that residents can smell food cooking. Some may sit at the table while personnel prepare breakfast, which naturally triggers conversation: "Do you want eggs today or simply toast?" "Orange juice or tea?"
From an ADL viewpoint, this environment uses versatility in timing and format. A resident who wakes earlier might have a light first breakfast, then join others later for coffee and a pastry. Somebody with innovative dementia might be calmer with 3 or four smaller meals and snacks, served when they reveal interest, instead of being expected to consume three big plates on a precise clock.
Texture modifications and unique diets are easier to individualize when the cook is preparing meals for eight rather of eighty. You can have one plate pureed, one sliced, and one regular without frustrating the kitchen. Staff can likewise discover patterns: Joe consumes much better when his tablets are given after breakfast, not before; Maria consumes more when her water is flavored with a slice of lemon.
This is also where respite care remains become a chance to test and improve regimens. When a household sends out a parent for a week of respite care in a small home, attentive staff might recognize that the "bad cravings" reported in your home is partly a function of timing, solitude, or the way food is presented. That insight can travel back home with the household, or may notify an irreversible relocation if needed.
Medication and health regimens that fit the person
Medication management tends to look standardized from the exterior: times, does, blister packs. Customization appears in the method medications are woven into daily life and how negative effects are noticed.
For example, a diuretic given too late at night might ensure night time restroom trips and poor sleep. In a small home, caregivers see the instant effect. They witness the resident shuffling to the bathroom at 2 a.m., then groggy at breakfast, and can flag this pattern to the nurse or doctor. Changing the timing to late early morning can significantly improve quality of life.
Similarly, pain medications for arthritis or persistent neck and back pain can be arranged to peak before the most active part of the day, or before a known trigger like bathing. That enables citizens to get involved more totally in their own ADLs instead of requiring total assistance.
Small groups also see state of mind and cognition variations related to medications: a new antidepressant that makes someone more participated in grooming, or a sedative that leaves them too drowsy to consume. These subtleties often get missed in larger operations where different staff interact with the individual at various times and in various departments.
The function of relationships: connection as a clinical tool
Personalizing ADLs is not just about treatments. It depends greatly on stable relationships. In small homes, the same three to six caregivers often cover most shifts. Locals get used to the very same faces assisting them shower, dress, and relocation. That familiarity develops trust, which in turn makes intimate care less demanding and more effective.
I have watched a resident with advanced dementia withstand bathing from a brand-new staff member, then unwind almost instantly when a familiar caregiver took control of. There was no magic phrase. It was the body language, tone of voice, and shared history: "It's me, Anna, the one who constantly sings your church songs while we wash your hair."
Continuity also assists personnel acknowledge small changes that could signal health issues: a brand-new trembling when holding a tooth brush, wincing when raising an arm during dressing, or unstable transfers from chair to walker. These observations are often first made during ADLs, not throughout official assessments.
For families, this relational stability belongs to what differentiates great small homes from mediocre ones. High turnover undermines customization. A home that maintains caregivers for several years, not months, can collect a deep understanding of each resident's quirks and preferences.
Working with families before, during, and after move-in
Families arrive with their own regimens and stress factors. Some have actually been offering hands-on elderly look after years, waking several times in the evening to help with toileting or roaming. Others are actioning in after an abrupt hospitalization. Small senior homes that excel at personalized ADLs generally involve families closely.
This starts even before admission, with honest discussions about what is working at home and what is not. A kid might describe his mother as "refusing showers," however when probed, it turns out she just declines when he attempts to help and withstands far less when a female caretaker is included. That information forms staffing assignments.
Respite care is an effective tool here. Brief stays, frequently lasting a couple of days to a couple of weeks, allow the home to learn the person while giving the family a break. During respite, staff can explore timing, series, and approaches to ADLs. They may find that Dad accepts toileting support much better if used right after his mid-morning coffee, or that Mom eats twice as much when she sits next to someone who chats gently.
After a relocation, families require routine feedback, not almost medical issues but about day-to-day routines. A good small home will share particular observations: "Your father actually likes picking between 2 shirts instead of having a full closet to look at. It appears to reduce his frustration when dressing." These details assure households that their loved one is seen as an individual, not a list of tasks.
Questions families can ask to judge real personalization
Families visiting small senior homes frequently hear similar expressions: "We provide personalized care." "We treat your loved one like household." To find out whether that is true in practice, particular, concrete concerns help.
Here are useful questions to ask throughout a tour or care conference:
- How do you choose what time each resident awakens and goes to bed?
- Who picks clothes every day, and how do you handle it if a resident's choice is not practical?
- Can you describe how you assist somebody who is modest or fearful with bathing?
- What happens if my parent does not want to consume at the arranged mealtime?
- How do you include households in upgrading routines when health or abilities change?
The answers should consist of examples, not just policies. Listen for stories that show personnel notification and react to individual quirks.
Red flags that routines are not truly tailored
Personalized ADLs leave traces visible to an attentive visitor. Similarly, generic care has its own indications. When I speak with households, I encourage them to watch for a few caution patterns.
- Everyone wakes, consumes, and showers at the exact same times, without any exceptions mentioned.
- Staff refer mainly to "our residents" instead of using names and describing private preferences.
- You see multiple homeowners in mismatched or stained clothing, or with unshaven faces and unbrushed hair, without an excellent explanation.
- Bathrooms smell strongly of urine on repeated visits, suggesting rushed or badly timed continence care.
- When you inquire about your loved one's routine, personnel quote the care plan however struggle to explain what in fact occurred yesterday.
Any one of these might have an innocent factor on an offered day, but a pattern recommends a job focused culture instead of an individual focused one.
The quiet advantages: security, mood, and realistic independence
When activities of daily living are customized carefully in a small senior home, the benefits are easy to undervalue due to the fact that they look normal. Falls decrease because mobility assistance is aligned with how the person really moves. Skin remains healthy since bathing and continence care are proactive and considerate. Cravings enhances because meals match individual routines and rhythms.
Families frequently report that a parent appears "more themselves" after moving into a small, individualized assisted living home, regardless of the anticipated losses of aging. Part of that effect comes from social connection. Another part comes from the simple relief of having help with ADLs that feels supportive rather than infantilizing.
Personalized routines have limits. Not every choice can be honored every time. Personnel burnout and turnover remain risks, specifically in underfunded settings. Some residents require such extensive physical support that options should be narrowed for security. Still, within those restraints, small homes that deal with ADLs as the fabric of every day life, not a checklist, provide older grownups a quieter however profound gift: the capability to go through ordinary tasks in a way that still seems like their own.
For households weighing choices in senior care, it helps to look beyond the sales brochures and ask, "What will early mornings feel like here? How will my mother be assisted to bathe, dress, eat, utilize the restroom, move, and handle her health day after day?" In an excellent small home, the answer sounds less like a schedule and more like a story about one specific person. That is where real customization lives.
BeeHive Homes of Lamesa TX provides assisted living care
BeeHive Homes of Lamesa TX provides memory care services
BeeHive Homes of Lamesa TX provides respite care services
BeeHive Homes of Lamesa TX supports assistance with bathing and grooming
BeeHive Homes of Lamesa TX offers private bedrooms with private bathrooms
BeeHive Homes of Lamesa TX provides medication monitoring and documentation
BeeHive Homes of Lamesa TX serves dietitian-approved meals
BeeHive Homes of Lamesa TX provides housekeeping services
BeeHive Homes of Lamesa TX provides laundry services
BeeHive Homes of Lamesa TX offers community dining and social engagement activities
BeeHive Homes of Lamesa TX features life enrichment activities
BeeHive Homes of Lamesa TX supports personal care assistance during meals and daily routines
BeeHive Homes of Lamesa TX promotes frequent physical and mental exercise opportunities
BeeHive Homes of Lamesa TX provides a home-like residential environment
BeeHive Homes of Lamesa TX creates customized care plans as residents’ needs change
BeeHive Homes of Lamesa TX assesses individual resident care needs
BeeHive Homes of Lamesa TX accepts private pay and long-term care insurance
BeeHive Homes of Lamesa TX assists qualified veterans with Aid and Attendance benefits
BeeHive Homes of Lamesa TX encourages meaningful resident-to-staff relationships
BeeHive Homes of Lamesa TX delivers compassionate, attentive senior care focused on dignity and comfort
BeeHive Homes of Lamesa TX has a phone number of (806) 452-5883
BeeHive Homes of Lamesa TX has an address of 101 N 27th St, Lamesa, TX 79331
BeeHive Homes of Lamesa TX has a website https://beehivehomes.com/locations/lamesa/
BeeHive Homes of Lamesa TX has Google Maps listing https://maps.app.goo.gl/ta6AThYBMuuujtqr7
BeeHive Homes of Lamesa TX has Facebook page https://www.facebook.com/BeeHiveHomesLamesa
BeeHive Homes of Lamesa has an YouTube page https://www.youtube.com/@WelcomeHomeBeeHiveHomes
BeeHive Homes of Lamesa TX won Top Assisted Living Homes 2025
BeeHive Homes of Lamesa TX earned Best Customer Service Award 2024
BeeHive Homes of Lamesa TX placed 1st for Senior Living Communities 2025
People Also Ask about BeeHive Homes of Lamesa TX
What is BeeHive Homes of Lamesa Living monthly room rate?
The rate depends on the level of care that is needed. We do an initial evaluation for each potential resident to determine the level of care needed. The monthly rate is based on this evaluation. There are no hidden costs or fees
Can residents stay in BeeHive Homes until the end of their life?
Usually yes. There are exceptions, such as when there are safety issues with the resident, or they need 24 hour skilled nursing services
Do we have a nurse on staff?
No, but each BeeHive Home has a consulting Nurse available 24 – 7. if nursing services are needed, a doctor can order home health to come into the home
What are BeeHive Homes’ visiting hours?
Visiting hours are adjusted to accommodate the families and the resident’s needs… just not too early or too late
Do we have couple’s rooms available?
Yes, each home has rooms designed to accommodate couples. Please ask about the availability of these rooms
Where is BeeHive Homes of Lamesa TX located?
BeeHive Homes of Lamesa is conveniently located at 101 N 27th St, Lamesa, TX 79331. You can easily find directions on Google Maps or call at (806) 452-5883 Monday through Sunday 9:00am to 5:00pm
How can I contact BeeHive Homes of Lamesa TX?
You can contact BeeHive Homes of Lamesa by phone at: (806) 452-5883, visit their website at https://beehivehomes.com/locations/lamesa/, or connect on social media via Facebook or YouTube
Pedroza's Restaurant offers casual dining in a welcoming setting ideal for assisted living, memory care, senior care, elderly care, and respite care visits.